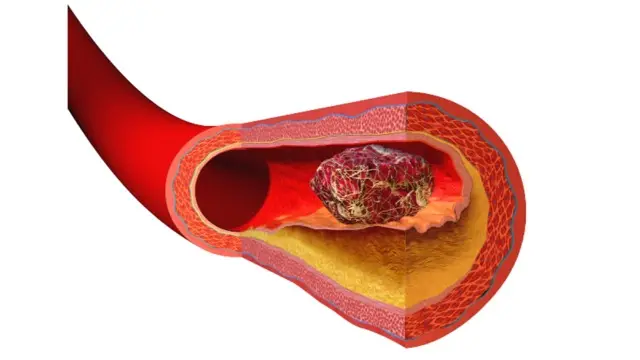
A venous ulcer is an open sore on the lower leg that forms because the leg veins are not working properly. It is the most advanced result of long-standing vein disease and the most common type of leg ulcer. This page explains what a venous ulcer is, what causes it, what it looks like, how it is diagnosed and what the outlook is. It is educational and cannot diagnose you. If you have a sore on your leg, please have it assessed.
What is a venous ulcer?
A venous ulcer, also called a venous leg ulcer, is a shallow wound on the leg, most often on the inner side of the lower shin or just above the ankle, that has not healed after about two weeks. The skin breaks down and the sore is usually slow to close. Without proper treatment it can stay open for months or return repeatedly.
You may also see it called a venous stasis ulcer or “stasis ulcer venous” in medical writing. “Stasis” means that blood has stopped flowing well and is stagnating in the veins. The phrase venous insufficiency ulceration describes the same thing from a different angle, meaning ulcers that develop because of chronic venous insufficiency.
What causes venous ulcers and venous stasis ulcers?
Healthy leg veins have one-way valves, and the calf muscles pump blood upwards when you walk. When valves fail, blood flows backwards and pools, a problem called venous reflux. Sometimes the cause is blockage in the veins, for example after a deep vein clot.
Either way, pressure in the veins of the lower leg stays high for long periods, which doctors call venous hypertension. Over time this:
- pushes fluid and blood cells out of the tiny vessels into the skin and tissue;
- causes inflammation and iron deposits that stain the skin brown;
- stiffens and thins the skin, so even a small knock or scratch may not heal;
- reduces the delivery of oxygen and nutrients to the skin.
An ulcer is often the end result of a long process, not a sudden event. Many people have had years of swelling, aching or varicose veins beforehand.
Risk factors include:
- varicose veins and a family history of vein disease;
- a previous deep vein thrombosis;
- older age;
- excess weight;
- limited ankle movement or reduced mobility;
- long periods of standing or sitting;
- previous leg injury, surgery or fracture.
Venous leg ulcer symptoms: what to look for
The ulcer itself is often preceded by warning signs on the lower leg. Check for:
- swelling around the ankle that builds through the day;
- aching, heaviness or itching;
- brown or reddish-brown staining of the skin around the ankle;
- dry, red, scaly or eczema-like skin (venous eczema);
- skin that has become hard, tight and shiny, sometimes called lipodermatosclerosis;
- small white scar-like patches (atrophie blanche).
When an ulcer forms it is typically:
- on the inner lower leg or ankle;
- shallow with uneven edges;
- surrounded by stained or inflamed skin;
- covered by yellowish slough or red tissue;
- moist and weeping;
- sometimes painful, but often more aching than sharp.
Venous ulcer pictures: what does it look like?
People often search for venous ulcer pictures. Photographs in medical textbooks and the NHS pages show the same general pattern, so here is a description in words rather than an image. A typical venous leg ulcer is a shallow, irregular wound with a ragged outline, a red or yellow base and darkened, thickened skin around it, usually near the inner ankle. The leg may look swollen and the surrounding skin may be itchy or scaly.
Photos can only go so far. Ulcers on the legs can have several causes, including poor arterial blood supply, diabetes, pressure and skin conditions, and these look different. Never rely on pictures to decide what you have. A clinician needs to examine the leg, check your pulses and often measure the blood pressure in your ankle. See our guide to arterial versus venous ulcers for the main differences.
Is a varicose vein ulcer different?
A varicose vein ulcer is a venous ulcer in someone who has visible varicose veins. The mechanism is the same: refluxing blood in superficial veins raises pressure in the lower leg. Leg ulcers can also happen when the varicose veins are barely visible or when the deep veins are involved. Our pages on varicose veins and the stages of varicose veins show how an ulcer sits at the advanced end of the disease.
How is a venous ulcer diagnosed?
Assessment usually includes:
- History and examination. Your doctor or nurse asks about swelling, previous clots, medications and how the sore started, and examines the skin.
- Checking the arteries. Because compression can be harmful if the leg has poor arterial blood flow, clinicians commonly check pulses and measure an ankle-brachial pressure index (ABPI) or similar test before applying strong compression.
- Duplex ultrasound of the veins. This shows where blood is flowing backwards or where veins are blocked and is central to planning treatment.
- Looking for other causes. Diabetes, infection, skin cancer and other conditions can resemble or complicate a venous ulcer. A wound that looks unusual or does not heal may need a biopsy.
NICE CG168 recommends referring people with a venous leg ulcer, whether active or healed, to a vascular service for assessment of the underlying veins. The ESVS 2022 guideline likewise recommends investigating and treating superficial venous reflux in people with venous ulcers.
Treatment and outlook in brief
The detail is covered in our page on venous ulcer treatment, but the main principles are:
- Compression therapy to reduce swelling and venous pressure, applied once arterial supply has been checked.
- Wound care with suitable cleaning and dressings, ideally guided by a trained nurse or clinician.
- Treating infection when present.
- Treating the vein problem. Closing refluxing veins with modern minimally invasive procedures such as vein ablation or sclerotherapy can lower the risk of the ulcer returning, according to guideline evidence. See treatments compared.
- Staying active. Walking and ankle exercises help the calf muscle pump work.
Venous ulcers generally heal slowly, and the time varies a lot between people, depending on size, age, mobility, other health conditions and how consistently compression is used. Recurrence is common if the underlying cause is not dealt with. People with recurrent venous ulcers often benefit from a specialist review. For a clear explanation of the condition and its management, you may also find this guide to venous leg ulcers useful.
Complications
- Infection. Spreading redness, warmth, swelling, pus, a bad smell or fever suggest infection such as cellulitis. See the NHS page on cellulitis for signs.
- Pain and poor sleep, which affect mood and daily activities.
- Dermatitis around the wound, from dressings, creams or leakage.
- Rarely, a long-standing ulcer can change in the tissue, which is one reason non-healing sores should be checked.
Reducing your risk
If you have swollen ankles, skin changes or varicose veins, acting early lowers the chance of an ulcer. Helpful steps include seeing a doctor about symptoms, wearing compression stockings if advised (see our compression stockings guide), keeping moving, raising your legs when resting, looking after your skin and keeping a healthy weight. Read how to prevent varicose veins for more.
When to see a doctor
See a doctor promptly if you have:
- any sore on the leg or ankle that has not healed within about two weeks;
- brown staining, hardening, eczema or persistent swelling near the ankle;
- a leg ulcer that is getting larger, smells, or is increasingly painful;
- redness spreading up the leg, with warmth, pus or fever.
Call 995 if you feel very unwell, faint or confused with a leg wound, if bleeding will not stop with firm pressure, or if you develop sudden chest pain, breathlessness or coughing blood. A swollen, painful, warm leg may also need urgent assessment for a clot.
Not sure whether your symptoms fit vein disease? Try our vein symptom check, and read about choosing a vein specialist.
Frequently asked questions
What is a venous ulcer?
A venous ulcer is a shallow open sore, usually on the inner lower leg or ankle, that is slow to heal. It develops when the veins cannot return blood to the heart efficiently, so pressure builds up and damages the skin from within.
Is a venous stasis ulcer the same as a varicose vein ulcer?
They overlap. A varicose vein ulcer is a venous ulcer in a person who has varicose veins. Not everyone with a venous ulcer has visible varicose veins, as reflux can occur in veins that are not visibly swollen.
Do venous ulcers hurt?
Often they ache, throb or feel heavy, especially when the leg is down, and the pain may ease when the leg is raised. Some ulcers are relatively painless. Sudden worsening pain may mean infection.
Can a venous ulcer heal on its own?
Small, early ulcers sometimes improve, but without treating the swelling and vein pressure they usually heal slowly and often return. Assessment and compression therapy are generally needed.
Are venous ulcers serious?
They are a sign of advanced vein disease and can become infected, painful and long-lasting, affecting sleep and daily life. With good care most can heal, but they need proper medical management.
Sources and further reading
This article is general information, not personal medical advice. Please speak to a doctor about your own symptoms. How we create our content.